

High blood pressure is often called a “silent” condition because many people feel completely well even when their blood pressure has been elevated for years. But the absence of symptoms does not mean that the body is unaffected. Over time, uncontrolled hypertension can damage blood vessels throughout the body, including the tiny blood vessels that allow the kidneys to filter waste from the blood.
This kidney damage is commonly referred to as hypertensive nephropathy or hypertensive kidney disease. It can develop gradually and may eventually contribute to chronic kidney disease (CKD) and kidney failure.
The good news is that kidney damage related to hypertension is often manageable, particularly when high blood pressure is detected and treated early. Controlling blood pressure, identifying protein in the urine, monitoring kidney function and addressing other cardiovascular risk factors can help slow or prevent further deterioration.
What is hypertensive nephropathy?
Hypertensive nephropathy is kidney damage caused by long-standing or poorly controlled high blood pressure. Persistent pressure against the walls of the kidney’s small arteries and arterioles can cause them to become thickened, narrowed and less flexible.
As blood flow through the kidney becomes impaired, the filtering structures called glomeruli can be damaged. Continued injury can lead to scarring, loss of functioning nephrons and a gradual decline in the kidneys’ ability to remove waste and excess fluid.
Modern research also shows that hypertensive kidney injury is more complicated than blood-vessel damage alone. Persistent hypertension can contribute to glomerular injury, tubular injury, inflammation and fibrosis within kidney tissue.
Hypertensive nephropathy is closely associated with hypertensive nephrosclerosis, a term used to describe structural kidney changes associated with hypertension.
It is important to remember that hypertension and kidney disease can also influence each other. High blood pressure can damage the kidneys, while kidney disease can make blood pressure more difficult to control.
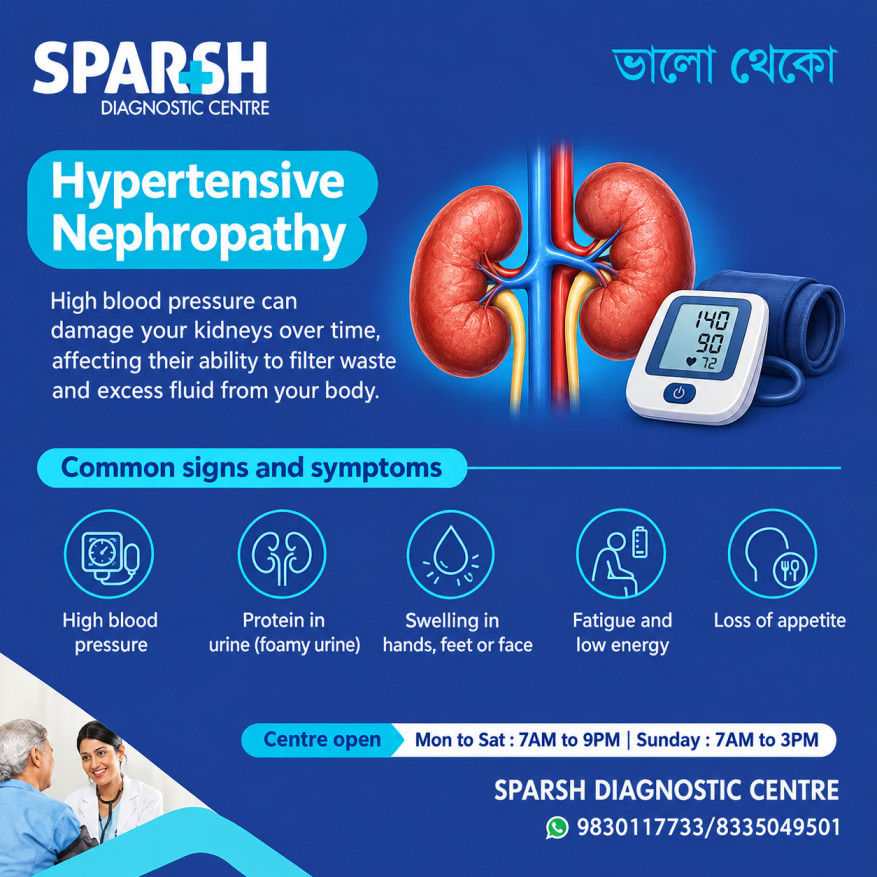
Can high blood pressure damage the kidneys?
Yes. High blood pressure can damage the kidneys, especially when it remains elevated over a long period.
The kidneys contain an enormous network of small blood vessels. Their job is to continuously filter the blood and maintain the body’s balance of fluid, electrolytes and waste products.
When blood pressure remains high:
- The walls of small kidney blood vessels can become thickened and damaged.
- Blood flow to parts of the kidney may become impaired.
- The glomeruli can become injured and scarred.
- Protein may begin to leak into the urine.
- Kidney filtration can gradually decline.
- Fluid and waste products may accumulate in the body.
Research on hypertensive kidney disease describes changes involving the arterioles, glomeruli, podocytes and tubulointerstitial tissue.
This is why managing blood pressure is an important part of protecting kidney health.
What causes hypertensive nephropathy?
The central cause is persistent high blood pressure, but the risk of kidney damage depends on several factors.
Important contributors include:
- Long-standing uncontrolled hypertension
- Severe or resistant hypertension
- Diabetes
- Obesity
- Smoking
- High dietary sodium intake
- Physical inactivity
- High cholesterol and other cardiovascular risk factors
- Existing chronic kidney disease
- Family history of hypertension or kidney disease
- Older age
Not everyone with hypertension develops severe kidney disease. The likelihood of progression is influenced by how high the blood pressure is, how long it remains uncontrolled and whether other kidney or cardiovascular risk factors are present.
What are the symptoms of hypertensive kidney disease?
One of the biggest challenges is that early hypertensive kidney disease may cause no noticeable symptoms.
As kidney function declines, symptoms may become more apparent. Possible symptoms include:
- Foamy or bubbly urine
- Swelling around the eyes, hands, feet or ankles
- Frequent urination, particularly at night
- Changes in urine volume
- Fatigue or low energy
- Loss of appetite
- Nausea
- Itchy or dry skin
- Difficulty concentrating
- Muscle cramps
- Sleep problems
- Shortness of breath in advanced disease
- Increasing blood pressure
These symptoms are not specific to hypertensive nephropathy. Other kidney, heart and metabolic conditions can cause similar symptoms, so testing is necessary rather than relying on symptoms alone.
What are the four warning signs of a damaged kidney?
If you want a simple checklist, four signs worth paying attention to are:
- Foamy or unusually bubbly urine — this can indicate excess protein in the urine.
- Swelling — particularly around the eyes, ankles, feet or hands.
- Changes in urination — such as urinating more frequently at night or producing substantially more or less urine.
- Persistent fatigue or weakness — particularly when kidney function has declined significantly.
However, kidney disease can exist without any of these symptoms. Routine blood pressure checks and kidney testing are therefore particularly important for people with hypertension.
What is renal hypertension?
Renal hypertension is high blood pressure caused by a kidney problem. It is different from hypertensive nephropathy, where high blood pressure is the cause of kidney injury.
Renal hypertension can occur when the kidneys cannot regulate blood pressure properly. One important cause is renal artery stenosis, in which an artery supplying a kidney becomes narrowed and reduces blood flow. Other kidney diseases can also contribute to secondary hypertension.
The distinction is useful:
Hypertension → kidney damage → hypertensive nephropathy
versus
Kidney disease or reduced kidney blood flow → hypertension → renal/secondary hypertension
In some people, both processes occur at the same time.
Can renal hypertension be cured?
It depends on the underlying cause.
If renal hypertension results from a treatable condition, addressing that condition may significantly improve blood pressure. For example, renal artery stenosis can be managed using medication and, in selected cases, procedures designed to improve blood flow.
However, if the underlying kidney disease has caused permanent damage, treatment may focus on controlling blood pressure and preventing further loss of kidney function rather than providing a complete cure.
What are 5 risk factors for hypertension?
Five important risk factors are:
- Older age
- Family history of high blood pressure
- Overweight or obesity
- High-sodium or unhealthy diet
- Physical inactivity
Smoking, excessive alcohol consumption, diabetes and certain medical conditions or medications can also increase risk.
These risk factors matter in hypertensive nephropathy because the factors that promote hypertension can indirectly increase the likelihood of long-term kidney injury.
How is hypertensive nephropathy diagnosed?
There is no single test that establishes hypertensive nephropathy in every patient. Doctors generally combine the medical history, blood pressure measurements, urine tests, blood tests and other investigations.
Common tests include:
Blood pressure measurement
Repeated, properly performed blood pressure measurements are important because one isolated high reading does not necessarily establish chronic hypertension.
Home blood pressure monitoring may also help doctors understand a person’s usual blood pressure outside the clinic.
Serum creatinine and eGFR
A blood test measures creatinine. The result can be used to estimate the glomerular filtration rate (eGFR), which provides an indication of kidney filtering capacity.
Urine albumin-to-creatinine ratio
A urine ACR can identify albumin leakage into the urine. Albuminuria is an important marker of kidney damage and helps assess the risk of CKD progression.
Other tests
Depending on the individual situation, a doctor may recommend:
- Electrolyte testing
- Blood glucose and HbA1c
- Lipid profile
- Urinalysis
- Kidney ultrasound
- Renal artery imaging when renovascular disease is suspected
- Additional kidney investigations when another cause of CKD is possible
The objective is not simply to confirm that the kidneys are affected but also to determine why they are affected and how advanced the disease is.
What are the stages of hypertensive nephropathy?
There isn’t a universally accepted staging system specifically called the “stages of hypertensive nephropathy.” In clinical practice, kidney damage caused or associated with hypertension is generally assessed using the chronic kidney disease (CKD) staging system, based primarily on eGFR and albuminuria.
A simplified eGFR classification is:
| CKD category | eGFR (mL/min/1.73 m²) | General description |
|---|---|---|
| G1 | ≥90 | Normal or high, but kidney damage may still be present |
| G2 | 60–89 | Mildly decreased |
| G3a | 45–59 | Mild to moderately decreased |
| G3b | 30–44 | Moderately to severely decreased |
| G4 | 15–29 | Severely decreased |
| G5 | <15 | Kidney failure |
Importantly, G1 or G2 alone does not necessarily mean CKD. There must generally be evidence of kidney damage, such as persistent albuminuria, or another marker of kidney abnormality.
KDIGO recommends assessing both eGFR and albuminuria when evaluating CKD and its risk of progression.
At what blood pressure does kidney damage start?
There is no single blood pressure number at which kidney damage suddenly begins.
Kidney and blood-vessel risk generally increases as blood pressure becomes higher and remains elevated for longer. Current American Heart Association guidance classifies:
- Normal: below 120/80 mmHg
- Elevated: 120–129 systolic and below 80 diastolic
- Stage 1 hypertension: 130–139 systolic or 80–89 diastolic
- Stage 2 hypertension: 140 or higher systolic or 90 or higher diastolic
This does not mean that everyone with a reading of 130/80 has kidney damage. Rather, persistent hypertension increases long-term risk.
A reading above 180/120 mmHg is considered severe hypertension. If it is accompanied by symptoms such as chest pain, shortness of breath, weakness, vision changes or difficulty speaking, it may represent a hypertensive emergency requiring immediate medical attention. Severe hypertension can damage organs including the kidneys.
How is hypertensive nephropathy treated?
Treatment focuses on two goals: controlling blood pressure and protecting remaining kidney function.
1. Blood pressure control
Blood pressure treatment is central to managing hypertensive kidney disease.
The 2025 AHA/ACC hypertension guideline identifies a general treatment goal of below 130/80 mmHg for adults, while individual targets may vary depending on the patient’s age, health conditions, tolerance and clinical circumstances.
For people with CKD, KDIGO emphasizes individualized blood pressure management and, when tolerated with standardized measurement, suggests a systolic target below 120 mmHg in appropriate adults with high BP and CKD. This differs from the AHA/ACC framework and illustrates why the target should be individualized rather than self-selected.
2. ACE inhibitors or ARBs when appropriate
Renin-angiotensin-system medicines, including ACE inhibitors and ARBs, are particularly important in CKD when albuminuria is present.
KDIGO recommends or suggests RAS inhibition in people with CKD and moderately to severely increased albuminuria, depending on whether diabetes is present. ACE inhibitors and ARBs should not be combined with each other.
These medicines should be prescribed and monitored by a healthcare professional because kidney function and potassium levels may need checking after treatment begins or the dose changes.
3. Reduce sodium intake
Reducing excessive salt intake can help with blood pressure and fluid management. Dietary recommendations should be individualized, particularly in advanced CKD where potassium, fluid and other nutritional requirements may need attention.
4. Maintain a healthy weight
If a person is overweight, gradual weight management can contribute to better blood pressure control and lower cardiovascular risk.
5. Exercise regularly
Appropriate physical activity can support cardiovascular health and blood pressure control. People with advanced CKD or other medical conditions should discuss the safest exercise plan with their healthcare professional.
6. Stop smoking
Smoking damages blood vessels and adds cardiovascular risk. Stopping smoking is an important part of protecting both the heart and kidneys.
7. Control diabetes and cholesterol
When hypertension occurs alongside diabetes, high cholesterol or other metabolic problems, managing these conditions becomes part of the overall kidney-protection strategy.
How is nephrosclerosis treated?
Nephrosclerosis cannot usually be reversed once significant permanent scarring has developed, but its progression can often be slowed.
Treatment generally includes:
- Effective blood pressure control
- Appropriate antihypertensive medication
- ACE inhibitor or ARB therapy when clinically indicated, particularly with albuminuria
- Sodium reduction
- Smoking cessation
- Weight management
- Diabetes control where applicable
- Regular monitoring of eGFR and urine albumin
- Management of cardiovascular risk factors
Current clinical guidance emphasizes blood pressure management as a major component of treatment for hypertensive nephrosclerosis.
Can lowering blood pressure improve kidney function?
Sometimes, yes—but it depends on the type and extent of kidney damage.
Lowering uncontrolled blood pressure can reduce ongoing stress on the kidney’s blood vessels and filtering structures. In some people, kidney function can stabilize or even improve after blood pressure is brought under better control. Historical clinical research has documented improvement in renal function after intensive blood pressure management in some patients with hypertensive nephrosclerosis.
However, established scarring and loss of functioning kidney tissue cannot necessarily be reversed.
The practical goal is therefore not simply to “increase eGFR.” It is to control blood pressure, reduce albuminuria where possible, prevent further damage and preserve kidney function for as long as possible.
How to stop nephropathy from getting worse?
You cannot always completely stop kidney disease, but you can often reduce the rate at which it progresses.
Key steps include:
- Keep blood pressure within the target set by your healthcare professional.
- Take prescribed medicines consistently.
- Monitor urine albumin and kidney function.
- Reduce excessive dietary sodium.
- Maintain a healthy body weight.
- Stay physically active as medically appropriate.
- Avoid smoking.
- Control blood sugar if you have diabetes.
- Manage cholesterol and cardiovascular risk factors.
- Avoid taking medicines such as NSAID painkillers regularly without discussing them with a healthcare professional, particularly if you have CKD.
- Attend scheduled kidney and blood pressure follow-ups.
Early detection makes a meaningful difference because kidney disease can progress quietly before symptoms become obvious.
What is the best sleeping position for kidney patients?
There is no single sleeping position proven to protect kidney function in everyone with kidney disease.
For most people, comfort and good-quality sleep matter more than choosing a particular side. Side sleeping may be comfortable for many people, while those experiencing breathing difficulty may find side sleeping or sleeping with the upper body elevated more comfortable.
If kidney disease is accompanied by significant swelling, breathlessness or difficulty breathing while lying flat, this should not simply be treated as a sleeping-position problem. It may indicate fluid overload or another medical issue and should be discussed promptly with a healthcare professional.
Can hypertensive nephropathy be prevented?
In many cases, the risk can be substantially reduced.
The most important preventive measure is early detection and effective management of high blood pressure.
Regular blood pressure checks are particularly important for people with diabetes, obesity, a family history of hypertension or kidney disease, cardiovascular disease, or other risk factors.
A heart-healthy diet, reduced sodium intake, regular physical activity, healthy weight, avoidance of tobacco and appropriate alcohol intake can all support blood pressure control.
For people who already have hypertension, taking medication exactly as prescribed and monitoring blood pressure regularly can help prevent years of uncontrolled pressure from silently affecting the kidneys.
When should you see a doctor?
Speak with a healthcare professional if you have:
- Persistently high blood pressure
- Repeated readings of 140/90 mmHg or higher
- Diabetes with hypertension
- Foamy urine
- Blood in the urine
- New swelling of the feet, ankles or face
- Significant changes in urination
- Unexplained fatigue
- Abnormal creatinine or eGFR results
- Increasingly difficult-to-control blood pressure
If blood pressure is above 180/120 mmHg, repeat the measurement after at least one minute. If it remains that high, contact a healthcare professional promptly. If it is accompanied by chest pain, shortness of breath, weakness, numbness, vision changes or difficulty speaking, emergency medical care is required.
Frequently asked questions about hypertensive nephropathy
Can high blood pressure damage the kidneys?
Yes. Long-standing uncontrolled hypertension can damage the small blood vessels and filtering structures of the kidneys, potentially leading to chronic kidney disease and kidney failure.
What is hypertensive nephropathy?
Hypertensive nephropathy is kidney damage associated with persistent high blood pressure. It can involve vascular injury, glomerular damage, inflammation and fibrosis and may gradually reduce kidney function.
What is renal hypertension?
Renal hypertension refers to high blood pressure caused by kidney disease or impaired blood flow to the kidneys. Renal artery stenosis is one possible cause.
How is nephrosclerosis treated?
Treatment focuses primarily on controlling blood pressure, reducing cardiovascular risk, managing albuminuria when present and addressing associated conditions such as diabetes. Significant established scarring may not be reversible, so early treatment is important.
Can lowering blood pressure improve kidney function?
It can sometimes stabilize or improve kidney function, particularly when uncontrolled hypertension is contributing to the decline. However, established kidney scarring may be permanent.
What are the symptoms of hypertensive kidney disease?
Early disease may have no symptoms. Later symptoms can include foamy urine, swelling, fatigue, changes in urination, poor appetite, itching, nausea and sleep or concentration problems.
Can renal hypertension be cured?
Sometimes the underlying cause can be treated and blood pressure may improve substantially. If permanent kidney disease remains, however, long-term blood pressure management may still be necessary.
What are the four warning signs of a damaged kidney?
Foamy urine, swelling, changes in urination and persistent fatigue are four important warning signs. They are not specific to kidney disease, so appropriate testing is necessary.
What are 5 risk factors for hypertension?
Five common risk factors are older age, family history, excess weight, an unhealthy/high-sodium diet and physical inactivity. Smoking, excessive alcohol use and certain medical conditions also increase risk.
What is the best sleeping position for kidney patients?
There is no universally recommended kidney-specific sleeping position. Choose a comfortable position that allows good-quality sleep. If lying flat causes breathlessness, seek medical advice rather than simply changing your sleeping position.
How do you stop nephropathy from getting worse?
Control blood pressure, follow prescribed treatment, monitor eGFR and urine albumin, reduce excessive sodium, avoid smoking, maintain a healthy weight, exercise appropriately and manage diabetes and other cardiovascular risk factors.
What are the stages of hypertensive nephropathy?
There is no separate universally accepted staging system for hypertensive nephropathy. Kidney involvement is generally assessed using CKD categories based on eGFR and albuminuria, ranging from G1 through G5.
At what blood pressure does kidney damage start?
There is no precise threshold at which kidney damage suddenly begins. Persistent hypertension increases risk over time. Current AHA/ACC guidance defines stage 1 hypertension as 130–139 systolic or 80–89 diastolic, while readings above 180/120 are considered severe and can be associated with acute organ damage.
Final thoughts
Hypertensive nephropathy often develops quietly, which makes prevention and regular testing especially important. A person may feel perfectly healthy while elevated blood pressure is gradually affecting the kidney’s blood vessels and filtering structures.
The most useful approach is not to wait for symptoms. Know your blood pressure, monitor kidney function when appropriate, check urine albumin, take prescribed medication consistently and address other cardiovascular risk factors.
The earlier high blood pressure and kidney abnormalities are identified, the more opportunity there is to slow progression and preserve kidney function.
Medical disclaimer: This article is intended for general health education and does not replace an evaluation by a qualified doctor. Blood pressure targets, medicines, dietary restrictions and kidney treatment should be individualized according to the person’s kidney function, albuminuria, age, other medical conditions and treatment tolerance.
#BhaloTheko
Disclaimer:
No content on this site, regardless of date, should ever be used as a substitute for direct medical advice from your doctor or other qualified clinician.


